Teeth Grinding (Bruxism) and Dental Work: Veneers, Crowns, Implants and Night Guards
Meet the Stom Dental Centre team
Being told you grind your teeth can sound like a verdict: no veneers, no implants, a guard for life. The research is less dramatic and, in places, more uncomfortable than the folklore. Grinding is associated with a higher risk of failure for some kinds of dental work, the size of that risk depends on the kind of work, and the thing that is so often recommended, the night guard, has less proof behind it than most people assume.
This article goes through what is actually known: what bruxism is, how sure anyone can be that you have it, and how veneers, crowns, implants and night guards fare in studies. Most of the evidence is observational, so we point out where it is thin.
- According to the dental consensus, bruxism is a behaviour, not a disease. The 2025 international consensus defines it as repetitive jaw-muscle activity (clenching, grinding, bracing) during sleep or while awake, and says dentists assess it rather than diagnose it.
- Worn teeth do not prove it, and neither does “I grind”. In a laboratory study, self-reported grinding did not predict moderate or severe sleep bruxism, and in a sleep-recording study tooth wear was not linked to the number of grinding episodes.
- Veneers: higher failure in grinders in several studies (7.7 times in one clinic), but the certainty is very low, and other ceramic work showed no clear effect. Enamel preservation matters too.
- Implants: pooled studies report roughly two to five times higher failure odds and more mechanical complications in grinders. All observational; one older review judged a biological risk unlikely.
- Night guards: no randomised trial has measured tooth wear in adults, and guards do not reliably stop grinding. Protection is expected, not proven, and the observational veneer data favour wearing one.
What Bruxism Is, and What It Is Not
The 2018 international consensus describes sleep bruxism as muscle activity of the chewing muscles during sleep, either rhythmic or sustained, and awake bruxism as repetitive or sustained tooth contact and/or bracing or thrusting of the jaw. In otherwise healthy people it should not be regarded as a disorder but as a behaviour that can be a risk, a neutral or even a protective factor (Lobbezoo 2018). The 2025 update goes a step further: bruxism is a motor behaviour that clinicians assess, together with its possible consequences, but do not diagnose like a disease. The old grading of “possible, probable, definite” was replaced by three kinds of assessment: by the person’s own report, by clinical examination and by devices such as EMG or sleep recordings (Verhoeff 2025). In some people grinding is a sign of something else, such as sleep apnoea, REM sleep behaviour disorder or epilepsy.
How common is it? That depends on how you ask. A meta-analysis of 176 studies, most of them questionnaires, pooled 21% for sleep bruxism and 23% for awake bruxism, with a wide range between studies and only four studies based on sleep recordings (Zieliński 2024). A systematic review of adult studies found “frequent” sleep bruxism in 12.8% (Manfredini 2013). No figure for Turkey was reported in the pooled reviews.
Do Worn Teeth Prove It? Does “I Grind” Prove It?
Neither is as reliable as it feels. A scoping review of 30 publications found no or weak associations between tooth wear and bruxism in most studies, with cervical wear the exception, and concluded that clinicians should not infer bruxism from tooth wear alone (Bronkhorst 2024). In 63 patients with possible sleep bruxism who wore an ambulatory sleep-recording unit at home for one night, tooth wear was not associated with the number of bruxism episodes per hour (P = 0.381), and the authors point to erosion, abrasion and daytime habits as other causes of wear (Kapagiannidou 2021). Self-report fares no better: in a study of 124 women with chronic jaw-muscle pain and 46 controls, self-reported sleep bruxism did not significantly predict moderate or severe sleep bruxism on the sleep-laboratory recording (it did predict two or more grinding sounds in the women with jaw-muscle pain), and its authors advise using it with extreme caution (Raphael 2015). Wear can also be historical; it tells you what happened over years, not what happened last night.
In practice that means a careful dentist combines the history, the signs and, sometimes, a recording, and treats the answer as an estimate.
Night Guards: What They Can and Cannot Do
A night guard is the default answer to grinding, and the evidence behind it is thin. A Cochrane review from 2007 found only five small trials (about 9 to 21 participants) of poor methodological quality and concluded that there was not enough evidence that a splint is effective for sleep bruxism, with possibly some benefit for tooth wear (Macedo 2007). A 2020 review of 37 trials of splints (almost all in temporomandibular disorders, that is, jaw-joint and chewing-muscle problems) found no trial that measured tooth wear in patients with bruxism, and rated the certainty as very low (Riley 2020). Two small adult studies that were not part of that review, and that are not described as randomised, cannot settle the question: in 10 adults with nocturnal bruxism, the crown length of the upper incisors shrank less over four years in the five who wore a splint for six months than in the five who did not (Korkut 2020), and in 16 adults who all wore splints, measurable tooth wear still occurred over 18 months (Laksamikeeratikul 2025). In a six-week recording study of 16 grinders, grinding events fell significantly right after the splint was inserted, but not after 2, 4 or 6 weeks (Harada 2006).
Hard or soft? In a 1987 experiment with 10 participants a hard splint reduced night-time muscle activity in 8 of 10; a soft splint reduced it in 1 and increased it in 5 (Okeson 1987). Guards may not be entirely free of side effects either, although the one signal we found is small: in a randomised crossover trial of 10 patients with obstructive sleep apnoea, a stabilisation splint raised the average number of breathing interruptions per hour from 15.9 to 17.4, an increase the authors called small, which reduces its clinical relevance (Nikolopoulou 2013).
Where guards look useful is in protecting restorations, and the evidence comes from veneer cohorts. In a retrospective study of 323 veneers in 70 patients, all 30 grinders were told to wear a hard splint and 15 did: 1 of the 89 veneers in the 15 who wore it fractured, against 7 of the 81 veneers in the 15 who did not (P = 0.023), while debonding did not differ (Granell-Ruíz 2014). In a prospective study of 364 veneers, veneers in grinders who wore a splint had an 89.1% survival at 7 years against 63.9% in grinders without one (Faus-Matoses 2020). These are observational findings, and people who wear their guard may differ from those who do not. The expert view, as summarised in 2019 by Matthias Lange and Ingrid Peroz in the German dental journal zm, in an article explaining the German S3 guideline on bruxism, is that a protective splint should be used after prosthetic rehabilitation in sleep bruxism, preferably a hard, full-coverage one (Lange and Peroz 2019). The guideline was revised in 2026 (zm-online 2026), and we could not check whether this recommendation changed. We found no systematic data on how many people keep wearing their guard in the long run; in the veneer cohort above, only half of the grinders (15 of 30) wore the guard they had been told to wear.

Veneers: A Higher Risk in Some Studies, but How High?
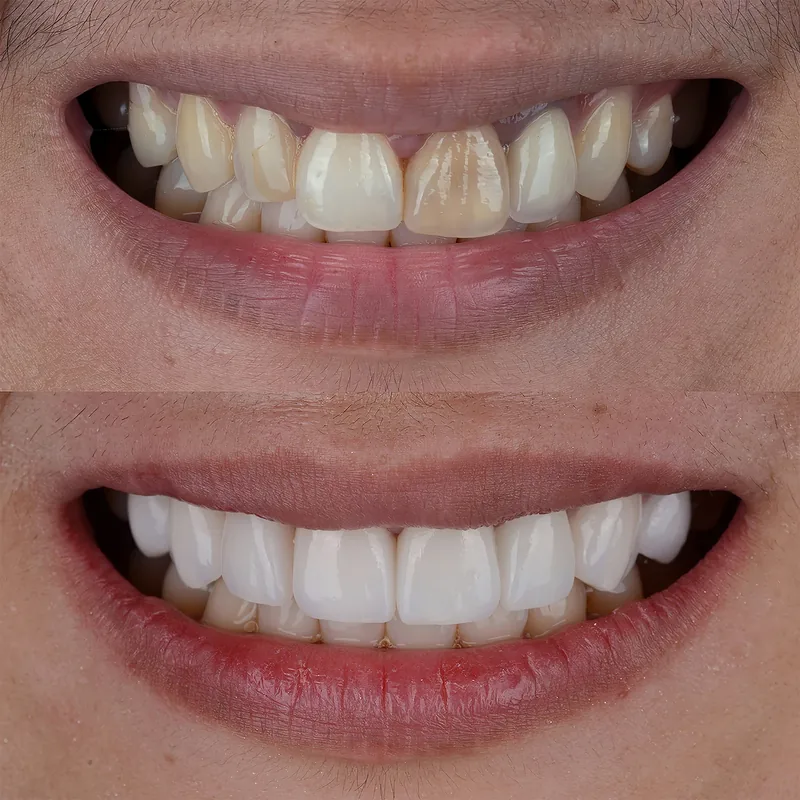
In a university clinic in Innsbruck, 318 glass-ceramic veneers in 84 patients were followed for an average of almost ten years. Survival was 94.4% at 5 years, 93.5% at 10 years and 82.9% at 20 years; teeth with a dead nerve failed more often, and existing parafunction such as bruxism went with a 7.7 times higher risk of failure (Beier 2012). In Valencia, 30 of 70 patients were grinders, and they accounted for 22 of the 29 veneers that debonded (Granell-Ruíz 2014). A systematic review of eight studies (five of them pooled in the meta-analysis) found a hazard ratio of 7.74 for anterior veneers in grinders, but no clear association for other ceramic restorations (odds ratio 1.10; 95% CI 0.43–2.8) and rated the certainty of the evidence as very low (de Souza Melo 2018).

Two points keep this in proportion. First, how much enamel is left matters too: in a series of 580 veneers, those bonded to dentin or with dentin at the margins were about ten times more likely to fail than enamel-bonded ones (99% survival for enamel-confined preparations against 94% when only the margins were in enamel), and wear did not significantly influence failure (Gurel 2013). Second, survival figures depend on who reports them. A meta-analysis of 29 studies found about 96% survival at a mean follow-up of 10.4 years (the long-term estimate rests on nine of the studies, 1,688 veneers; Klein 2025), but in routine general dental practice in England and Wales only 53% of 2,562 veneers survived ten years without re-intervention (Burke and Lucarotti 2009). Published series often apply selection criteria, and the endpoints differ (clinical survival versus re-intervention), so the figures are not directly comparable; the routine-care figure is much lower.
Our guides to veneers and laminate veneers describe the procedure.
Crowns: One Trial, With No Detectable Effect but Small Groups
Only one randomised trial has looked at crowns and sleep bruxism. It enrolled 109 patients who needed a single molar crown, in four groups: monolithic lithium disilicate or zirconia, with or without sleep bruxism (assessed by questionnaire, examination and portable EMG). The four groups in the three-year report add up to 93 patients. After three years survival was 96.3% and 100% for lithium disilicate and 95.2% and 95.8% for zirconia (grinders and non-grinders respectively); success was 81.5%, 95.2%, 85.7% and 95.8%. The differences were not significant, but the groups were small, 21 to 27 patients each (Bömicke 2026).
Monolithic crowns (made from one block of ceramic) chip less than veneered ones: in a review of 64 studies, 5-year survival was 98.5% for monolithic lithium disilicate and 96.8% for monolithic zirconia, against 97.1% for metal-ceramic, and monolithic crowns had fewer ceramic fractures (Pjetursson 2026). The abstract of that review does not mention grinding. Observational studies give a mixed picture: in a two-year study of 95 monolithic zirconia posterior restorations (85 of them on implants), 80% of the catastrophic failures were in patients with clinical signs of bruxism, who made up 61.7% of the patients, and the authors found the failure rate of single-unit restorations not as high as expected (Koenig 2019). In a retrospective study of 507 implant-supported units in 144 patients, 24 of the 34 patients with at least one fracture of the ceramic veneering were grinders (P = .002; Mikeli 2016). A scoping review (Saracutu 2026) found no randomised trial that compared the long-term success of restoration materials in people with different degrees of bruxism (the trial above only split patients into grinders and non-grinders), so claims that one material is the grinder’s choice go beyond the evidence.
For materials, see our pages on zirconia crowns and e.max against zirconia.
Implants: Higher Odds, Weak Data
A meta-analysis of 10 publications counted 49 failures among 760 implants in grinders (6.45%) and 109 among 2,989 in non-grinders (3.65%), a risk ratio of 2.93 (95% CI 1.48–5.81); its authors still said the data were too limited to prove an effect (Chrcanovic 2015). A 2024 meta-analysis of 27 studies that included only people with at least “probable” bruxism found an odds ratio of 2.19 (95% CI 1.34–3.58): 138 failures among 2,105 implants in grinders against 352 among 10,264 in non-grinders (Häggman-Henrikson 2024). In a specialist-clinic cohort of 3,549 implants in 994 patients, failure was 13.0% in grinders and 4.6% in non-grinders, a hazard ratio of 3.4 after adjustment (Chrcanovic 2016). Two further meta-analyses reported odds ratios of about 3.8 to 4.7 (Zhou 2016: 3.83 per patient, 4.72 per prosthesis; Ionfrida 2024: 4.68). Mechanical problems are where the signal is strongest: a 2025 meta-analysis found higher odds in grinders for ceramic fracture (4.36), screw loosening (3.40), abutment fracture (13.88) and implant fracture (16.14); its abstract gives no confidence intervals, so read the largest values as a direction, not a size (Vidal 2025).
The picture is not uniform. A systematic review of 21 papers (published online in 2012, so older than the meta-analyses above) concluded that bruxism is unlikely to be a risk factor for biological complications (implant failure, implant mobility and bone loss), with some suggestion of a mechanical risk (Manfredini 2014). Every figure above comes from observational studies in which bruxism was defined differently, so they show an association, not what a guard or a different design would change.
Our implant guide describes the procedure, and our article on peri-implantitis covers the biological complications.
Full-Mouth Rebuilds Are Not a Treatment for Bruxism
We found no evidence that rebuilding the bite stops grinding. A systematic review found no clinical trials of prosthetic treatment in patients with temporomandibular disorders (jaw-joint and chewing-muscle problems) or bruxism and advised care with irreversible changes to the bite in them (Manfredini and Poggio 2017). The German guideline summary goes further: definitive occlusal measures, such as grinding teeth to adjust the bite or rebuilding it with restorations, should not be used for the causal treatment of bruxism (Lange and Peroz 2019). Case series of grinders treated with zirconia rehabilitations (veneered and non-veneered) report good short-term results, such as 99.6% survival of restorations after a mean of 28 months in 10 patients, with veneer chipping in 13.9% of the veneered restorations (Levartovsky 2019), but they have no control groups.

Botulinum Toxin, Medicines and Habit Work
Botulinum toxin injections into the chewing muscles are used off-label for bruxism: the German guideline summary of 2019 said they may be considered in adults, with attention to off-label use and professional regulations (Lange and Peroz 2019; the guideline was revised in 2026). A 2026 meta-analysis of five placebo-controlled trials with 101 participants found fewer grinding events and lower muscle-activity readings, yet only one of six studies that also measured frequency by questionnaire, global impression or sleep recording found a clear toxin-specific benefit (Val 2026). No drug is recommended: a 2026 meta-analysis of nine studies concluded that no medication can be recommended for routine management (Li 2026). Some antidepressants have been linked to grinding in case reports (Garrett 2018). For awake clenching, a 2026 systematic review rated the evidence for reminders and for biofeedback as low certainty, each resting on a single small randomised trial (Graham 2026).
Botulinum toxin also appears in our article on gummy smile treatment, where its use for a different problem is discussed. For extensive rebuilding of the bite, see full-mouth reconstruction.
A UK Case, and What to Ask Before Work Begins
A case from the files of the UK dental defence organisation MDDUS, published in Scottish Dental magazine, shows what can go wrong when grinding is missed. A 54-year-old had veneers on several upper and lower teeth plus two crowns; several veneers came off within weeks. The claim alleged that the raised risk of failure with bruxism had not been explained, and an expert felt that a mouth guard before the veneers, or full-coverage crowns, would have been more appropriate. The claim was settled (Craig 2017). One case is not a statistic, but the questions it raises are sensible:
Planning dental treatment in Antalya?
Get a free, no-obligation assessment from our clinical team — we reply within 24 hours.
- How was my grinding or clenching assessed, and what did the examination show?
- Will I need a protective guard, which type, and who makes it?
- For veneers: how much enamel will remain, and is a less invasive or reversible option sensible first?
- Are provisional restorations or a trial period planned before anything permanent?
- What happens if something chips or debonds, and are the warranty terms in writing?
Frequently Asked Questions
Is bruxism a disease?
According to the 2025 international consensus (and, for otherwise healthy people, the 2018 one), no: it is a behaviour that can be a risk, neutral or protective factor. Clinicians assess it together with its consequences and treat the consequences, or an underlying disorder such as sleep apnoea (Lobbezoo 2018; Verhoeff 2025).
Does worn enamel prove that I grind my teeth?
No. Studies, including overnight sleep recordings, found weak or no association between tooth wear and current grinding, and wear has other causes such as acids and abrasion (Bronkhorst 2024; Kapagiannidou 2021).
Can I have veneers if I grind my teeth?
Grinders had higher failure rates in several cohorts, including a 7.7-times higher risk of failure in one clinic, but the certainty of the evidence is very low and we found no consensus statement that lists it as a contraindication. Enamel preservation, an assessment of the grinding and a protective guard matter (Beier 2012; de Souza Melo 2018; Gurel 2013).
Are zirconia or lithium disilicate crowns safe for grinders?
In the only randomised trial (109 patients enrolled, 93 analysed after three years) neither material showed a detectable effect of sleep bruxism, but the groups were small (Bömicke 2026). A scoping review found no trial that compared materials across different degrees of bruxism (Saracutu 2026).
Do implants fail more often in people who grind?
Meta-analyses of observational studies report roughly two to five times higher failure odds and more mechanical complications such as ceramic or screw problems; one older review judged a biological risk unlikely. Treat it as an association, not a prediction for you (Häggman-Henrikson 2024; Zhou 2016; Ionfrida 2024; Manfredini 2014; Vidal 2025).
Will a night guard stop my grinding and protect my new teeth?
It does not reliably stop grinding, and no randomised trial has measured tooth wear in adults. Veneer cohorts found fewer failures in grinders who wore a splint (fewer fractures in one cohort, better overall survival in the other), and the German guideline summary recommends a protective guard after rehabilitation, preferably hard and full-coverage (Macedo 2007; Riley 2020; Harada 2006; Granell-Ruíz 2014; Faus-Matoses 2020; Lange and Peroz 2019).
Do botulinum toxin injections or medicines help?
The toxin lowers muscle activity for weeks to months but evidence for fewer grinding events or symptoms is mixed, and its use is off-label. No medication is recommended (Val 2026; Li 2026; Lange and Peroz 2019).
Sources
- Lobbezoo F, Ahlberg J, Raphael KG, et al. International consensus on the assessment of bruxism: report of a work in progress. J Oral Rehabil. 2018;45(11):837-844. doi:10.1111/joor.12663. PMID 29926505.
- Verhoeff MC, Lobbezoo F, Ahlberg J, et al. Updating the bruxism definitions: report of an international consensus meeting. J Oral Rehabil. 2025;52(9):1335-1342. doi:10.1111/joor.13985. PMID 40312776.
- Zieliński G, Pająk A, Wójcicki M. Global prevalence of sleep bruxism and awake bruxism in pediatric and adult populations: a systematic review and meta-analysis. J Clin Med. 2024;13(14):4259. doi:10.3390/jcm13144259. PMID 39064299.
- Manfredini D, Winocur E, Guarda-Nardini L, Paesani D, Lobbezoo F. Epidemiology of bruxism in adults: a systematic review of the literature. J Orofac Pain. 2013;27(2):99-110. doi:10.11607/jop.921. PMID 23630682.
- Bronkhorst H, Kalaykova S, Huysmans MC, Loomans B, Pereira-Cenci T. Tooth wear and bruxism: a scoping review. J Dent. 2024;145:104983. doi:10.1016/j.jdent.2024.104983. PMID 38574847.
- Kapagiannidou D, Koutris M, Wetselaar P, Visscher CM, van der Zaag J, Lobbezoo F. Association between polysomnographic parameters of sleep bruxism and attrition-type tooth wear. J Oral Rehabil. 2021;48(6):687-691. doi:10.1111/joor.13149. PMID 33474786.
- Raphael KG, Janal MN, Sirois DA, et al. Validity of self-reported sleep bruxism among myofascial temporomandibular disorder patients and controls. J Oral Rehabil. 2015;42(10):751-758. doi:10.1111/joor.12310. PMID 26010126.
- Macedo CR, Silva AB, Machado MA, Saconato H, Prado GF. Occlusal splints for treating sleep bruxism (tooth grinding). Cochrane Database Syst Rev. 2007;(4):CD005514. doi:10.1002/14651858.CD005514.pub2. PMID 17943862.
- Riley P, Glenny AM, Worthington HV, et al. Oral splints for temporomandibular disorder or bruxism: a systematic review. Br Dent J. 2020;228(3):191-197. doi:10.1038/s41415-020-1250-2. PMID 32060462.
- Korkut B, Tagtekin D, Murat N, Yanikoglu F. Clinical quantitative evaluation of tooth wear: a 4-year longitudinal study. Oral Health Prev Dent. 2020;18(4):719-729. doi:10.3290/j.ohpd.a45075. PMID 32895655.
- Laksamikeeratikul I, Jariyasakulroj S, Chattrattrai T, Pongrojpaw S. Digital measurement of tooth wear in sleep bruxism patients wearing occlusal splints. BMC Oral Health. 2025;25(1):1349. doi:10.1186/s12903-025-06716-6. PMID 40841662.
- Harada T, Ichiki R, Tsukiyama Y, Koyano K. The effect of oral splint devices on sleep bruxism: a 6-week observation with an ambulatory electromyographic recording device. J Oral Rehabil. 2006;33(7):482-488. doi:10.1111/j.1365-2842.2005.01576.x. PMID 16774505.
- Okeson JP. The effects of hard and soft occlusal splints on nocturnal bruxism. J Am Dent Assoc. 1987;114(6):788-791. doi:10.14219/jada.archive.1987.0165. PMID 3475357.
- Nikolopoulou M, Ahlberg J, Visscher CM, Hamburger HL, Naeije M, Lobbezoo F. Effects of occlusal stabilization splints on obstructive sleep apnea: a randomized controlled trial. J Orofac Pain. 2013;27(3):199-205. doi:10.11607/jop.967. PMID 23882452.
- Granell-Ruíz M, Agustín-Panadero R, Fons-Font A, Román-Rodríguez JL, Solá-Ruíz MF. Influence of bruxism on survival of porcelain laminate veneers. Med Oral Patol Oral Cir Bucal. 2014;19(5):e426-e432. doi:10.4317/medoral.19097. PMID 23986018.
- Faus-Matoses V, Ruiz-Bell E, Faus-Matoses I, Özcan M, Salvatore S, Faus-Llácer VJ. An 8-year prospective clinical investigation on the survival rate of feldspathic veneers: influence of occlusal splint in patients with bruxism. J Dent. 2020;99:103352. doi:10.1016/j.jdent.2020.103352. PMID 32413382.
- Lange M, Peroz I. Was wir heute über Bruxismus wissen: S3-Leitlinie “Diagnostik und Behandlung von Bruxismus”. zm (Zahnärztliche Mitteilungen) 15/2019.
- zm-online. Bruxismus-Leitlinie: Was ist neu? 1 July 2026 (report on the updated S3 guideline “Diagnostik und Behandlung von Bruxismus”, version 2.1, 2026, AWMF register no. 083-027).
- Beier US, Kapferer I, Burtscher D, Dumfahrt H. Clinical performance of porcelain laminate veneers for up to 20 years. Int J Prosthodont. 2012;25(1):79-85. PMID 22259802.
- de Souza Melo G, Batistella EÂ, Bertazzo-Silveira E, et al. Association of sleep bruxism with ceramic restoration failure: a systematic review and meta-analysis. J Prosthet Dent. 2018;119(3):354-362. doi:10.1016/j.prosdent.2017.07.005. PMID 28967401.
- Gurel G, Sesma N, Calamita MA, Coachman C, Morimoto S. Influence of enamel preservation on failure rates of porcelain laminate veneers. Int J Periodontics Restorative Dent. 2013;33(1):31-39. doi:10.11607/prd.1488. PMID 23342345.
- Klein P, Spitznagel FA, Zembic A, et al. Survival and complication rates of feldspathic, leucite-reinforced, lithium disilicate and zirconia ceramic laminate veneers: a systematic review and meta-analysis. J Esthet Restor Dent. 2025;37(3):601-619. doi:10.1111/jerd.13351. PMID 39523553.
- Burke FJ, Lucarotti PS. Ten-year outcome of porcelain laminate veneers placed within the general dental services in England and Wales. J Dent. 2009;37(1):31-38. doi:10.1016/j.jdent.2008.03.016. PMID 18538912.
- Bömicke W, Schmitter M, Waldecker M, et al. Ceramic crowns and sleep bruxism: 3-year results of a randomized controlled trial. J Dent. 2026;170:106691. doi:10.1016/j.jdent.2026.106691. PMID 41967567.
- Pjetursson BE, Pitta J, Balet A, Bjarnadottir GR, Sailer I, Romandini P. A systematic review and meta-analysis evaluating the survival, failure, and complication rates of metal-ceramic, veneered, and monolithic all-ceramic tooth-supported single crowns, part 1. Int J Prosthodont. 2026;39(3):308-324. doi:10.11607/ijp.9633. PMID 41489982.
- Koenig V, Wulfman C, Bekaert S, et al. Clinical behavior of second-generation zirconia monolithic posterior restorations: two-year results of a prospective study with ex vivo analyses including patients with clinical signs of bruxism. J Dent. 2019;91:103229. doi:10.1016/j.jdent.2019.103229. PMID 31722238.
- Mikeli A, Walter MH. Impact of bruxism on ceramic defects in implant-borne fixed dental prostheses: a retrospective study. Int J Prosthodont. 2016;29(3):296-298. doi:10.11607/ijp.4610. PMID 27148995.
- Saracutu OI, Ferrari M, Pollis M, Manfredini D, Cagidiaco EF. The outcome of prosthodontic treatments in individuals with bruxism and different restoration material: a scoping literature review. Cranio. 2026;44(2):236-248. doi:10.1080/08869634.2025.2477964. PMID 40167462.
- Chrcanovic BR, Albrektsson T, Wennerberg A. Bruxism and dental implants: a meta-analysis. Implant Dent. 2015;24(5):505-516. doi:10.1097/ID.0000000000000298. PMID 26218253.
- Häggman-Henrikson B, Ali D, Aljamal M, Chrcanovic BR. Bruxism and dental implants: a systematic review and meta-analysis. J Oral Rehabil. 2024;51(1):202-217. doi:10.1111/joor.13567. PMID 37589382.
- Chrcanovic BR, Kisch J, Albrektsson T, Wennerberg A. Bruxism and dental implant failures: a multilevel mixed effects parametric survival analysis approach. J Oral Rehabil. 2016;43(11):813-823. doi:10.1111/joor.12431. PMID 27611304.
- Zhou Y, Gao J, Luo L, Wang Y. Does bruxism contribute to dental implant failure? A systematic review and meta-analysis. Clin Implant Dent Relat Res. 2016;18(2):410-420. doi:10.1111/cid.12300. PMID 25726844.
- Ionfrida JA, Stiller HL, Kämmerer PW, Walter C. Dental implant failure risk in patients with bruxism: a systematic review and meta-analysis of the literature. Dent J (Basel). 2024;13(1):11. doi:10.3390/dj13010011. PMID 39851587.
- Vidal RA, Martins VC, Figueiredo EZ, Roithmann CC, Bertuzzi D, Grossi ML. Relationship between bruxism and different types of mechanical complications in implant-supported prosthesis: a systematic review with meta-analysis. J Prosthodont. 2025. doi:10.1111/jopr.70046. PMID 41102936.
- Manfredini D, Poggio CE, Lobbezoo F. Is bruxism a risk factor for dental implants? A systematic review of the literature. Clin Implant Dent Relat Res. 2014;16(3):460-469. doi:10.1111/cid.12015. PMID 23151302.
- Manfredini D, Poggio CE. Prosthodontic planning in patients with temporomandibular disorders and/or bruxism: a systematic review. J Prosthet Dent. 2017;117(5):606-613. doi:10.1016/j.prosdent.2016.09.012. PMID 27836142.
- Levartovsky S, Pilo R, Shadur A, Matalon S, Winocur E. Complete rehabilitation of patients with bruxism by veneered and non-veneered zirconia restorations with an increased vertical dimension of occlusion: an observational case-series study. J Prosthodont Res. 2019;63(4):440-446. doi:10.1016/j.jpor.2019.02.006. PMID 30904358.
- Val M, Colonna A, Nykänen L, Pollis M. Effects of botulinum toxin injection on masticatory muscle activity in sleep bruxism: a systematic review and meta-analysis. J Clin Med. 2026;15(18):7179. doi:10.3390/jcm15187179. PMID 42795952.
- Li D, Chen H, Sun S, Jiayi L, Wei F. Pharmacologic management of sleep bruxism in adults: a systematic review and meta-analysis of polysomnographic outcomes. J Oral Rehabil. 2026;53(9):1783-1796. doi:10.1111/joor.70254. PMID 42402887.
- Garrett AR, Hawley JS. SSRI-associated bruxism: a systematic review of published case reports. Neurol Clin Pract. 2018;8(2):135-141. doi:10.1212/CPJ.0000000000000433. PMID 29708207.
- Graham DA, Lövgren A, Häggman-Henrikson B, Peck CC, Manfredini D, Saracutu OI. Management of awake bruxism: a systematic review. BMC Oral Health. 2026;26(1):559. doi:10.1186/s12903-026-07856-z. PMID 41735990.
- Craig A. Grinding patient makes veneers claim. Scottish Dental magazine, 10 April 2017 (MDDUS case study).
This article is for general information only and does not replace an individual dental examination or the advice of your treating dentist. The figures come from the independent publications listed under Sources; they describe groups of patients in specific studies, mostly observational, and are not a guarantee of outcome for any individual patient or clinic.